An Eyelid Lift Protects Visual Field and Facial Alertness
If you have droopy eyelids, you may need an eyelid lift to see better. Looking chronically fatigued even after eight hours of unbroken sleep is rarely just a cosmetic issue. In many cases, it points to a mechanical failure in the delicate elevator muscles responsible for hoisting your upper eyelids clear of your pupils.
Fixing an impaired eyelid hinge requires distinguishing between loose surface skin and genuine muscle weakness before choosing an intervention. If you are comparing surgical options for droopy eyelid treatment, exploring internal suture plication against formal external incisions gives you a clear baseline for balancing downtime against structural longevity. Addressing muscular laxity early restores your upper visual field while taking strain off your forehead muscles.
The Mechanics of An Upper Eyelid Lift
Your upper eyelid relies primarily on the levator palpebrae superioris muscle and its fibrous tendon to pull the eyelid margin upward. Working beneath it is Mueller’s muscle, an involuntary secondary helper that maintains baseline elevation during waking hours.
When prolonged contact lens wear, ageing, or genetics stretches the levator tendon, the muscle can no longer transmit pulling force to the eyelid margin. As the lid droops over the pupil, your brain automatically compensates by firing your forehead frontalis muscles, leading to chronic tension headaches and deep horizontal brow furrows.
Eyelid Lift Surgery: Which Is Better Suture Plication Or Open Incisional Surgery
Online guides frequently promote non-incisional scarless ptosis repair because it takes thirty minutes and allows you to return to work within four days. The non-obvious trade-off is that scarless repair relies on internal suture loops to tuck the conjunctiva and Mueller’s muscle without trimming redundant levator tendon.
Choosing an open incisional procedure trades two weeks of visible bruising for permanent anatomical advancement of the primary levator muscle. In mild cases with thin skin, non-incisional tucking works well. However, in moderate droopiness or thicker eyelids, suture loops gradually loosen under blinking friction, making open structural re-anchoring the far more dependable choice for long-term lid height.
The Double Eyelid Blepharoplasty Mistake
The most common and expensive mistake patients make is requesting a simple double eyelid crease surgery to fix an eye that looks tired. People fall into this trap because they assume that cutting away hooded skin will automatically make their eyes look bigger and brighter.
In reality, creating a double eyelid fold over an undiagnosed weak levator muscle actually worsens the drooping effect. The new fold sits directly over an eyelid that cannot lift itself, resulting in a heavy, half-asleep look with an unnaturally wide, hollow crease. Patients are then forced into revision surgery to dismantle the crease and tighten the muscle beneath it.
Calculating The Cost Of An Eyelid Lift And Lower Lid Surgery
Let us examine a concrete worked example comparing misdiagnosed cosmetic skin excision against correct primary ptosis repair over three years. Consider someone who spends 3,200 pounds on a standard upper blepharoplasty to fix their heavy-looking eyes.
Because the underlying levator tendon remains stretched, their pupils stay partially obstructed, and the newly carved crease droops lower by month eighteen. Correcting this requires complex scar tissue release and levator muscle advancement costing 6,500 pounds, bringing total outlay to 9,700 pounds across two painful recovery periods. In contrast, diagnosing muscular weakness accurately and undergoing primary ptosis repair costs 5,200 pounds upfront in a single session. Addressing the muscle directly saves 4,500 pounds while protecting your eyesight.
Practical Habits for Healthy Eyelid Function
Protecting your levator muscles from unnecessary mechanical stretching requires establishing simple, repeatable habits in your daily grooming routine. Treating your eyelids like delicate mechanical linkages keeps tendon friction low.
Keep these practical operational habits in mind:
- Avoid aggressive eyelid rubbing: Blot itchy eyes gently with a clean tissue rather than pulling downward on the upper lid.
- Insert contact lenses without pulling lids: Use gentle finger placement on the lower lid to avoid stretching the upper levator tendon.
- Limit continuous forehead compensation: Notice when you raise your eyebrows to read screens and adjust your monitor height downward to reduce eye elevation strain.
A Simple Rule for Eyelid Lift Assessment
You do not need an ophthalmology degree to evaluate whether your eyelid issue stems from loose skin or genuine muscle laxity. You can apply a straightforward decision rule called the brow-lock test in your bathroom mirror.
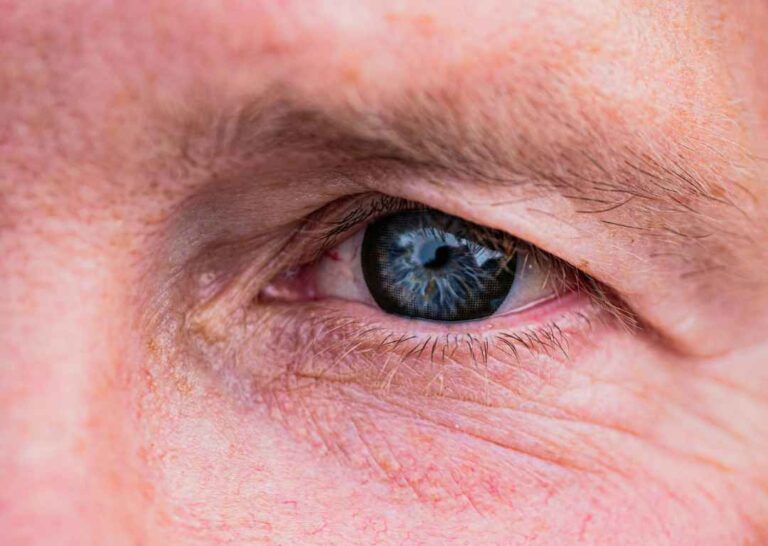
Place your thumb firmly across your eyebrow, pressing against your forehead bone so the brow cannot move upward, and look straight ahead into the mirror. If your eyelid naturally clears the top half of your pupil while your brow is locked down, your muscle is strong and you only have excess skin. If your eyelid droops over more than two millimetres of your black pupil when your eyebrow cannot help lift it, you have true ptosis that requires muscle plication or advancement.
Restoring healthy eyelid elevation is ultimately about selecting a targeted treatment that matches your underlying muscular anatomy. By avoiding the mistake of treating muscle weakness with surface skin removal, weighing the trade-offs of scarless tucking, and applying clear diagnostic rules, you protect both your visual comfort and your finances. Approach your surgical planning with calm strategy, rely on solid anatomical facts, and move forward with quiet confidence in your personal decisions.
More Health Articles To Read
Surprising Facts About Cheek Fat
Your Best Plan For Meniscus Knee Injury
6 Best Tips For Choosing Birth Control